Sunday, January 2, 2011

The Anatomy and Definition of Nasal Valve Collapse and Internal Valve Stenosis

Here is a simple explanation to describe the complexity of  Nasal Valve Collapse, from Drs Litner & Solieman's website: see link below with photo's.

The nasal valve is a term used to describe the narrowest part of the nose internally. This is the area that determines if someone feels normal or obstructed breathing through the nose. When this area is overly narrowed and blocked, we call it nasal valve collapse.  

There really are two types of nasal valve collapse. The collapse of the tip cartilages described above can cause external valve collapse where the blockage is just past the nostril. When most surgeons discuss valve collapse, though, they are talking about internal valve collapse. This occurs when the upper lateral cartilages in the middle of the nose have been too narrowed.  This problem happens when a nasal bump is taken down too much and when the cartilages themselves are shortened or not reattached during a Rhinoplasty. The problem seems to occur more often after a closed Rhinoplasty because most surgeons detach these cartilages without repairing and reattaching them at the end of the procedure. When the natural cartilage supports have been lost, they simply fall inwards and collapse. The result is poor breathing and two visible cosmetic deformities. One is called an ‘inverted V deformity’. That’s because the collapsed area where these cartilages attach to the nasal bones looks like an upside-down letter V. The second problem is that the middle part of the bridge can start to look very pinched.
http://www.rhinoplastyinbeverlyhills.com/rhinoplasty-mistake-8-nasal-valve-collapse

Dr. Craig Murakami explains that an internal nasal valve is considered to have collapsed when the angle of the valve is less than 10[degrees] to 15[degrees]. Its etiology can be congenital, traumatic, or iatrogenic. (1) In the latter case, collapse is often caused by over-resection of the nasal dorsum and upper lateral cartilages during septorhinoplasty. Such an overly aggressive operation can result in concurrent dorsal concavity (saddle-nose deformity) or a narrowing of the middle third of the nose (hourglass deformity).

 http://findarticles.com/p/articles/mi_m0BUM/is_3_83/ai_n6077596/

Important nose anatomy illustration diagrams from Dr. Beckers website. 

Rhinoplasty, Postrhinoplasty Nasal Obstruction  

Author:Thomas Romo III, MD, FACS 

Coauthor(s): James M Pearson, Haresh Yalamanchili, MD, Paul Presti M.D.

Grymer used acoustic rhinometry to evaluate the internal dimensions of the nasal cavity in 37 patients before reduction rhinoplasty and again 6 months after surgery.3 He demonstrated that rhinoplasty decreases the cross-sectional area of the nasal valve by 25% and the piriform aperture by 13%. Cole et al also used rhinomanometry to reveal that changes of as small as 1 mm to the nasal valve size can dramatically increase nasal resistance

Therefore, the nasal valve, as a regulator of nasal airflow and resistance, has been demonstrated to play a critical role in the function of the nose. Disturbance of the nasal valve area can produce limitations to normal nasal breathing. Multiple schemes can be used to classify the types of nasal valvular dysfunction. One convenient method is to group them according to either internal or external nasal obstruction (see Classification of nasal valve dysfunction). Kern and Wang divide the etiologies of nasal valve dysfunction into mucocutaneous and skeletal/structural disorders. The mucocutaneous component refers to the mucosal swelling (secondary to allergic, vasomotor, or infectious rhinitis) that can significantly decrease the cross-sectional area of the nasal valve and thus reduce nasal airway patency. The skeletal component can be further divided into static and dynamic nasal dysfunction.

In summary, nasal valve dysfunction can be secondary to either mucocutaneous problems or skeletal deformities (affecting either the internal or the external nasal valve), which can be dynamic or static. However, the cause is rarely so straightforward. In most instances, the mucocutaneous and skeletal components and the static and dynamic components contribute in varying degrees to the overall nasal valvular dysfunction.
Skeletal deformity:

Deformities that affect the internal nasal valve area
  • Static deformity
    • Inferomedially displaced upper lateral cartilage
    • Narrowing of pyriform aperture
    • Scarring at intercartilaginous junction
    • Turbinate hypertrophy
    • Deviated nasal septum
  • Dynamic deformity - Collapsed upper lateral cartilage secondary to disruption of support from the nasal bone, septum, and lower lateral cartilage
Because ventilation involves pressure changes, the nasal airways must be stable both at rest and under the negative pressures created during quiet and forced inspiration. The internal and external nasal valves depend on satisfactory skeletal stability of the upper and lower lateral cartilages, respectively. When either the skeletal or the soft tissue component is congenitally deficient or has been compromised by surgery or trauma, the patient experiences a dynamic collapse of the valve during inspiration, with resultant airway obstruction. Normally, the upper lateral cartilages partially collapse at a ventilatory flow rate of 30 L/min. Thus, even normal nasal valves collapse with vigorous respiratory effort; however, a patient with dynamic nasal valve dysfunction may have a lateral nasal wall that is so weakened that it collapses even during normal nasal breathing.

The internal nasal valve area is the narrowest portion of the nasal passage and thus functions as the primary regulator of airflow and resistance. The cross-sectional area of the nasal valve area is 55-83 mm2. As described by the Poiseuille law, airflow through the nose is proportional to the radius of the narrowest portion of the nasal passageway, raised to the fourth power. Thus, changes as small as 1 mm in the size of the nasal valve exponentially affect airflow and resistance through the nasal cavity.

http://emedicine.medscape.com/article/841574-overview#Classificationofnasalvalvedysfunction

Rhinoplasty, Internal Valve Stenosis
Author: David Núñez-Fernández, MD, PhD Co-Authors: Jan Vokurka, MD, PhD, Gloria Fernández-Muñoz, MD

The airflow resistance provided by the airways during breathing is essential for good pulmonary function. The nose is responsible for almost two thirds of this resistance. Most of this resistance occurs in the anterior part of the nose. This region is called the nasal valve, and it acts as a flow-limiter.

External nasal valve collapse can be found in patients without a history of trauma or surgery. These patients commonly have an overprojecting nose with extremely narrow nostrils. Another cause can be an extremely wide columella,

Internal nasal valve collapse can be divided depending on the structure that caused the collapse. In many cases, more than one structure is affected. The most common cause is probably septal deviation.  The second cause is collapse secondary to rhinologic surgery, especially after removal of the nasal roof. Khosh found, in 53 patients, the following causes of nasal valve collapse: previous rhinoplasty (79%), nasal trauma (15%), and congenital anomaly (6%).4

Upper lateral cartilage  (ULC)
Thickened cartilage can compromise an adequate aperture. The cartilage can also be twisted, deflected, or associated with excessive return of the caudal border. An absence of cartilage, either congenital or iatrogenic, can produce a flaccid valve that collapses during inspiration.

Lower lateral cartilage  (LLC)
Overresection during rhinoplasty can weaken the cartilage and cause inspiratory collapse. Deformation of the cartilage can be a result of trauma or congenital malformations of the cartilage.

Although uncommon, some patients may have deformities of the pyriform aperture that reduce the space of the nasal valve.

Rhinoplastic procedures are particularly prone to disturbing the nasal valve area. Hump removal affects the nasal valve in several ways. If the hump is particularly large, separation of the ULC can be necessary. Resection of the T-shaped area of the dorsal border of the septum produces a narrower area in the roof. If the mucosa in the valve is not protected during the surgery, which occurred with the use of many older techniques, scarring of the valve can lead to structure formation or stenosis of the valve.

In reduction rhinoplasties, the cross-sectional area of the overall nose is reduced. This increases the resistance to airflow. If the nasal valve is not properly repaired during the surgery, patients may report nasal obstruction after the surgery, even if this was not reported preoperatively. Overresection of the lower lateral cartilage can lead to pinching and inspiratory collapse.

Because it is the narrowest part of the nose, the nasal valve can be affected by minute alterations of the nasal anatomy that would not be important in other areas. 

The angle between the ULC and the nasal septum is 10-15° (normally in Caucasians). Internal nasal valve collapse occurs when, for some reason, this angle is diminished. The result is an increase in nasal resistance to airflow; consequently, the patient reports nasal obstruction. The opposite is known as ballooning. In this case, the nasal valve is excessively open.

The pyriform aperture continues the limit of the valve from the ULC to the floor. The head of the inferior turbinate is immediately posterior to the pyriform aperture and plays an important role in the function of the valve, which is the reason it is also considered part of the internal nasal valvehttp://emedicine.medscape.com/article/877468-overview


Identifying nasal valve dysfunction:
Diagnosis can be difficult if the physician does not visualize the valvular area. Examining the valve without disturbing it with a nasal speculum is important because the speculum usually opens the valve. Sometimes, trimming the vibrissae is necessary to obtain a clearer view of the valve. Another method is to use a 0° endoscope


The Cottle test is useful to evaluate nasal valve stenosis. The cheek of the evaluated side is gently pulled laterally with 1 or 2 fingers, which opens the valve.


NOTE: Cottle test can be nonspecific
The problem with the standard Cottle maneuver is the results can be nonspecific. Dr. Jack D.Sedwick mentions on his website that a straightforward narrowing of the nasal airway produced by septal deviation or turbinate hypertrophy is improved by the Cottle maneuver. Anterior rhinoscopy is also a poor means of accurately evaluating subtle changes in nasal valve anatomy; the dysfunctional nasal valve can be missed due to distortion from the nasal speculum.

A more precise diagnosis can be made based on direct inspection of valvular support during quiet and forced inspiration. Collapse at the internal nasal valve is usually diagnosed based on the identification of medialization of the caudal margin of the upper lateral cartilages due to negative pressure created upon inspiration through the nose. A fine swab or cerumen curette may be used to lateralize the upper lateral cartilage to confirm the presence of internal valvular collapse.

More recently, Hilberg et al introduced acoustic rhinometry as a noninvasive and reliable objective method for determining the cross-sectional area of the nasal cavity.7 Acoustic rhinomanometry is based on the analysis of sound waves reflected from the nasal cavities.

Also, analysis can be done before and after topical decongestants are applied, allowing discrimination of mucocutaneous versus structural blockage. Standards for age, race, ethnicity and sex have been recently published.
http://www.providence.org/alaska/medstaff/nasalvalve.htm

http://emedicine.medscape.com/article/841574-overview#Classificationofnasalvalvedysfunction

http://simple-med.blogspot.com/2009_02_01_archive.html

Click on diagrams below for larger view 
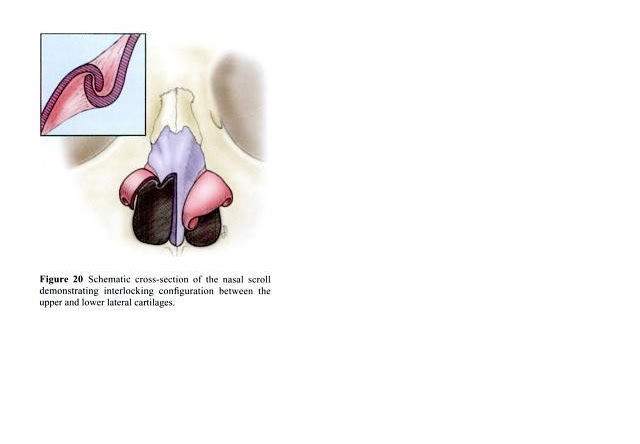
Note: Insert Picture, Upper and Lower Lateral Cartilage scrolls interlocking


Enhanced by Zemanta

Saturday, January 1, 2011

Viability of diced and crushed cartilage with different supportive sleeve material

Diced and crushed cartilage can be wrapped in different sleeve material. One of the main purposes for this is to camouflage irregular firm jagged edges of cartilage for a smoother cosmetic result especially in those with thin skin. Nose Revision Specialists have used the following materials as sleeves or fillers: Autogenous deep temporal fascia, Perichondrium, Surgicel (oxidized methylcellulose), dermal grafts, synthetic material and  esterified hyaluronic acid (HYAFF). A couple of study's have indicated the superiority of using deep temporal fascia or  esterified hyaluronic acid over surgicel (The Turkish delight method). I haven't come across any clinical experimental study's on Perichondrium  viability- reabsorption rate comparisons .  Dr. Eugene  A. Chu of John Hopkins University Dept. of Otolaryngology makes a recommendation to remove the perichondrium completely from the costal cartilage to limit warping, however Dr. Dean Toriumi, has claimed years of success with using perichondrium which will make the skin thicker and more importantly  help prevent graft visibility and deformity. Apparently it has given him a better long term outcome. Even though a few Surgeons have claimed success on long term follow up's with the Turkish delight method, most clinical studies indicate it is an inferior material to use, due to higher reabsorption rate of the contained cartilage.

According to Dr. Ozcan Cakmak and Dr. Fuat Buyuklu:

Some authors have stated that autogenous soft tissue grafts, such as dermal grafts3 or temporalis fascia grafts,5 are satisfactory for covering underlying dorsal irregularities. However, those materials have disadvantages of possible partial resorption and donor-site morbidity. Although some authors have suggested that temporalis fascia grafts are among the most reliable materials and are associated with reasonably low resorption rates,5, 8, 23 those grafts are difficult to manipulate because they are thin and slippery.23-24 Alloplastic materials, such as gelatin film,4 polyglactin 910 (Vicryl suture; Johnson & Johnson Gateway LLC, Piscataway, New Jersey),6 and Gore-Tex (W. L. Gore & Associates Inc, Newark, Delaware),7 have also been advocated for that purpose. However, absorbable synthetics do not last long, and of all graft materials, nonabsorbable synthetics are associated with the highest rates of infection and extrusion.2, 11 A soft-tissue filler, AlloDerm (LifeCell Corp, Branchburg, New Jersey), which is derived from cadaveric skin, is another material frequently used to achieve a smoother nasal dorsum. However, AlloDerm has the definite disadvantage of partial graft resorption, especially when it is positioned over the dorsum in patients with thin skin.

Although the maintenance of typical cartilage viability and a high graft survival rate have been reported with the use of this material, harvesting the temporalis fascia adversely affects the donor site, where either permanent or transient alopecia can develop after surgery.

Many authors have used bare crushed cartilage grafts to conceal dorsal irregularities and to achieve a smoother nasal surface.

http://archfaci.ama-assn.org/content/9/5/352.full

http://www.eclips.consult.com/eclips/article/Plastic-and-Aesthetic-Surgery/S1535-1513%2808%2970595-2

http://www.ncbi.nlm.nih.gov/pubmed/17690607

http://emedicine.medscape.com/article/881443-treatment

http://deantoriumi.com/faq1.asp

Saturday, December 25, 2010

Crushed vs Diced Cartilage: Similarities and Differences

Looking at some forums I noticed some people are using the words crushed and diced cartilage interchangeably as if they are same thing. Another important  issue i would like to address here is correlation between  the degree of crushed cartilage and how it effects the long term outcome (re absorption rate) of the surgery.

Crushing cartilage is procedure that takes pieces of cartilage and crushes it in a device called Cottle cartilage crusher and/or using a mallet. They can be crushed to varying degree's from slightly crushed to severely crushed. They are then inserted in the desired area of the nose using a medical tweezer.

Dicing cartilage is procedure where the cartilage is sliced using a straight edge razor blade into small fine pieces.  The cartilage is normally diced into <0.5mm squares, using two #11 blades avoiding, not being morselized or crushed. . Then it is placed in a syringe to be later injected in the desired area and molded/shaped accordingly. Usually diced cartilage  is wrapped in soft material preferably deep temporal fascia.

Both crushed and diced cartilage is used to smoothen out or camouflage nasal surface area's where cartilage is placed in the nose , like the dorsum, to conceal any irregularities. Both can be wrapped or combined with different material as well.

Crushed cartilage grafts can be used for the following purposes: (1) to cover the sharp edges of an irregular nasal framework after hump resection    (2) to serve as an underlying padding material to prevent skin adhesion   (3) to fill pit holes and, thus, mask irregularities   (4) as a filler to mask asymmetries and depressions on the side walls  (5) for tip grafting   (6) to camouflage the edges of solid onlay grafts  , (7) to supply minor dorsal augmentation for the correction of an overresected dorsum, and (8) to increase the thickness and natural color of the overlying skin where skin atrophy had occurred. I believe diced cartilage can be used in most of the above situations as well.

Crushed Cartilage Grafts for Concealing Irregularities in Rhinoplasty
  1. Ozcan Cakmak, MD;
  2. Fuat Buyuklu, MD

Our current clinical series confirmed our previous animal9 and human cell culture13 studies that the degree of crushing applied is important to the long-term clinical outcome of crushed cartilage grafts used in rhinoplasty.

The results showed a correlation between the degree of crushing applied and the resorption rate of the crushed graft, especially in grafts applied at the dorsum. The resorption rate was zero in slightly crushed grafts, 2.1% in moderately crushed grafts, and 13.1% in significantly crushed grafts. Our results show that slight or moderate crushing of the autogenous cartilage produces an outstanding graft material that is effective in concealing irregularities, filling defects, and creating a smoother surface, with excellent long-term clinical outcome and predictable esthetic result. We suggest that intact cartilage should be used to correct major deformities and that moderately crushed grafts should be used for smaller depressions to minimize resorption. The severely crushed form of cartilage should not be used as filler except to correct negligible depressions in atrophic skin.

The edges of solid onlay grafts might be softened by placing small pieces of moderately crushed grafts on or around the solid graft. The tiny pieces of moderately or significantly crushed grafts might be successfully used in final contouring at the conclusion of surgery. In patients with thin skin or in whom revision is required, a thin layer of moderately or significantly crushed cartilage would be the proper option as a padding material to prevent the adhesion of skin and to camouflage the sharp edges of the nasal skeleton that might be visible after edema has subsided.

From the above study,  one would presume that  thinner and smaller diced cartilage would also have higher resorption rates then thicker larger pieces, but I haven't seen any clinical studies to support or contradict that conclusion. 

http://archfaci.ama-assn.org/content/9/5/352.full

Wednesday, December 22, 2010

The Role of Diced Cartilage Grafts in Rhinoplasty

The fundamental technique for the use of diced cartilage in rhinoplasty has been known for over 50 years. One of the most impressive uses of diced cartilage is in cranioplasty, which demonstrates that the individual pieces coalesce into a semirigid graft over time. The term diced cartilage graft may refer to several different types of cartilage, methods of preparation, and methods of containment. In the present report, only autogenous cartilage derived from excised material, septum, or distant grafts is used. Containment refers to placement of the diced cartilage directly into a tight pocket for contour, layering of the cartilage on either side of rigid dorsal graft for blending, or placement of the cartilage in peripyriform pockets to advance the midface. The technique and benefits of diced cartilage grafts in rhinoplasty were reviewed.

A prospective study of more than 150 patients in 3 years found no evidence of absorption and no warping. Any problems thus far with the diced cartilage graft have been technical problems rather than problems with the graft material itself. One problem has been the visibility of radix grafts, particularly in patients with very active eyebrows. This problem is easily corrected by reduction with a pituitary rongeur or replacement with fascia alone. Dorsal grafts may have “edge show” cephalically, and caudally there may be inadequate grafting of the supratip region. This problem is easily corrected with the patient under local anesthesia by use of a pituitary rongeur. A minor depression may develop in the supratip area because the surgeon has initially undercorrected in pursuit of an immediate supratip break. This problem is corrected by keeping the graft truly full length rather than shortening it to get tip set off.
Conclusions: 
In using diced cartilage grafts in rhinoplasty, diced cartilage wrapped in fascia is simpler to use, quicker, and aesthetically superior to solid cartilage grafts, without risks of warping, malalignment, and K-wire extrusion.
 http://www.eclips.consult.com/eclips/article/Plastic-and-Aesthetic-Surgery/S1535-1513%2808%2970596-4

For the author,Rollin K. Daniel, MD; diced cartilage grafts have revolutionized dorsal grafts in rhinoplasty, replacing layered septal grafts, stacked conchal grafts, and carved costal cartilage grafts. He asserts that diced cartilage wrapped in fascia is simpler to use, quicker, and aesthetically superior to solid cartilage grafts, without risks of warping, malalignment and K-wire extrusion.

Diced cartilage grafts in rhinoplasty surgery: current techniques and applications. 

Dr.Rollin K. Daniel has used diced cartilage grafts in nasal surgery for more than 30 years. However, the number of cases and the variety of techniques have increased dramatically over the past 6 years.  

http://www.ncbi.nlm.nih.gov/pubmed/19050542


Autogenous Dorsal Reconstruction: Maximizing the Utility of Diced Cartilage and Fascia
Jay Calvert, M.D., F.A.C.S.1,2 and Kevin Brenner, M.D.2
 The problem of reconstructing the dorsum of the nose is complex and a source of frustration for both patients and surgeons. Dorsal deficiencies due to various etiologies and the need for dorsal contouring cause the plastic surgeon to look to time-honored techniques such as osseocartilaginous rib grafts while also searching for other options that may be less technically challenging and have the benefit of temporal success. Diced cartilage wrapped with deep temporal fascia is just such a method to achieve reliable dorsal reconstructions. The various ways to use diced cartilage and deep temporal fascia are discussed

The complications of using this technique are predictable and correctable. Because the cartilage is mobile for 10 to 14 days after placement, there can be defects that arise from poor management of the graft postoperatively. Edges are usually not visible, but they can be in a particularly thin-skinned patient. Overcorrection and undercorrection are probably the most common complications seen with this technique and must be managed accordingly. Malposition of the graft and mobility of the graft may also be seen in a rare number of cases. Absorption of the graft has not been seen in the longest of follow-ups (6 years).

In conclusion, the technique of diced cartilage with fascia (DC-F ) has been a useful method of dorsal reconstruction as a stand alone technique and in concert with other methods of building the dorsum. There are many permutations and surgical variations of the technique. The authors believe that proper preoperative analysis will help the surgeon to derive clear indications so that the correct graft variation is used with a clear purpose. There is no substitute for preoperative diagnosis and planning when using the DC-F graft. The technique is safe, easy to perform, has minimal morbidity, and is our favored method for addressing difficult problems in dorsal reconstruction.
Enhanced by Zemanta

Monday, December 20, 2010

Perichondrium vs Deep Temporal Fascia

When performing Augmentation or Revision nose surgery, soft tissue is needed. For instance it is used to cover cartilage used to build up area along the dorsum or tip or simply for augmenting an area, say's Dr. Paul Nassif. If doing Rib Harvesting, you can then use the Perichondrium which is soft tissue that lays on top of the rib instead of using temporal fascia. According to Dr. Nassif, it's a little more thicker, heavier, and firmer then Temporal fascia. He feels it's an excellent source of soft tissue. He also has a you tube video on how deep temporal fascia is harvested, but warning it is not for weak at heart. I assume he use's deep temporal fascia as a choice when not performing rib cartilage graft, to build up the radix or dorsum area's. This video  on harvesting Perichondrium.is less graphic, but still takes place in Operating Room.


Thursday, November 25, 2010

Allografts and the risks of infection and disease transmission

Here is some valuable information on the risks associated with implantation of allografts [i.e. cadaver grafts in nose surgery]

 AAOS 2004: All About Allografts -- Select Highlights of the 71st Annual Meeting of the American Academy of Orthopaedic Surgeons

 Controlling Infection is Crucial

In limiting infection during allograft procedures, it is important to determine whether the tissue bank that you or your hospital is using is a member of the American Association of Tissue Banks (AATB). This organization requires that its members perform full screening that meets US Food and Drug Administration requirements; however, secondary sterilization of the grafts is still optional. Not all tissue banks are members of AATB, and not all tissue banks are inspected. The review by Vangsness and colleagues[2] describes the process of procurement, processing, and storage, and should be required reading for anyone who is using allograft tissue. Be sure that you know your tissue bank and its procedures.
Infection of tissue can be controlled by screening the tissue donor and through secondary sterilization of the tissue. At this time, we can screen for both hepatitis B and C, which should prevent infection by these entities. There have only been 2 cases of HIV infection through allograft tissue, and both of these incidents occurred in the 1980s. These reported infections occurred with frozen bone as the vector, but none of the freeze dried grafts from the same donor transmitted the disease. The AATB has formulated guidelines for their members; these guidelines recommend donor screening.

There are a number of methods and federal guidelines for storing tissue after procurement. The methods of storing the tissue are: fresh frozen, deep frozen, freeze dried, demineralized, and proprietary treatments, such as CryoLife (CryoLife Inc., Kennesaw, Georgia

Factoring Relative Risk
The risk of hepatitis B after blood transfusion is 1/63,000. The risk of hepatitis C is 1/100,000, and the risk of HIV is 1/1,000,000. The risk of HIV after bone transplantation is 1/1,500,000. The risk of HIV after soft tissue transplantation is 1/1,600,000 with secondary sterilization.
To put this in the proper perspective, one should remember that the risk of death due to pregnancy is 1/10,000, the risk of death from administration of penicillin is 1/30,000, and the risk of death with oral contraceptives is 1/50,000. In fact, it may be more dangerous driving to the hospital than receiving a bone graft at the hospital.
In summary, allografts are a valuable treatment option for today's orthopaedic practice. The academy believes allografts to be safe if used within the guidelines, when they are supplied by an accredited tissue bank, and if the appropriate surgical techniques are employed.

How safe are soft-tissue allografts?

By C. Thomas Vangsness Jr., MD

 Although several cases of viral infection—specifically human immunodeficiency virus (HIV), viral hepatitis, and human T-lymphotropic virus (HTLV)—have been reported, these transmissions occurred before the guidelines for donor screening for viruses and bacteria were implemented and before the availability of currently validated serologic tests.

Sterility is expressed as a mathematic probability of relative risk. According to the FDA, a sterility assurance level (SAL) of 10-3 means there is a 1 in 1,000 chance that a nonviral viable microbe exists in or on the implanted material. The Association for the Advancement of Medical Instrumentation (AAMI) states that an SAL of 10-6 (one in a million chance) in organisms is more desirable. The American Association of Tissue Banks (AATB) requires an SAL of 10-6 for tissue bank allografts.

Contamination of the graft can also occur during the final handling and packaging of tissue. Gamma irradiation is commonly used to terminally sterilize allograft tissue with lower doses of radiation.

Freeze drying (lyophilization) is a preservation process that allows tissues to be stored at room temperature. Lyophilization freezes the tissue and reduces the water content to less than 6 percent of initial weight through a primary drying process (sublimation) and a secondary drying process (desorption). Although freeze-dried allografts (lyophilized grafts) are not commonly used for sports medicine applications in the United States, this process is commonly used with soft-tissue patches.

With improved donor screening techniques, such as nucleic acid testing (NAT), the current risk of transplanting tissue from an HIV-infected donor is reported to be between 1 in 1 million and 4 in 1 million.

According to a recent AATB survey covering data from 2003 to 2004, the current risk of an allograft infection to the average patient appears to be much less than the risk of infections surrounding the surgery itself. According to the report, there were 192 reports of suspected allograft-related infections in 2003-2004; 42 percent involved soft-tissue grafts and 37 percent involved bone grafts, with an overall incidence of 0.014 percent. Currently, better reporting of infections is actively under investigation to improve the accuracy of these numbers.

Do not do routine culturing of allograft tissue in the operating room immediately prior to implantation. These cultures are documented to be inaccurate and may reflect the native airborne or backtable contamination.

Musculoskeletal tissue regeneration: biological materials and methods  By William S. Pietrzak, Charles A. Vacanti

Although the risk is low, bacteria, hepatitis, HIV, and syphilis can be transmitted from donor to recipient. There is also the theoretical possibility of transmitting slow viruses (prions) with allograft use.
Irradiation of the soft tissue allografts with high dose (>3Mrad) radiation can sterilize allograft tissue, destroying bacteria and viruses including HIV and hepatitis. Bone plug allografts may still be capable of transmitting hepatitis despite treatment with 3 Mrad irradiation. Although, allograft irradiation will reduce the risk of disease transmission, it does so at the expense of diminishing the biomechanical properties of the tissue. Newer screening tests such as polymerase chain reaction (PCR) and nucleic acid testing (NAT) improve the detection of viral and bacterial DNA and RNA, and many increase the accuracy of identifying infected donor tissue and minimizing false-negatives. By improving the sensitivity and specificity of infected donor  tissue identification, the risk of bacterial and viral disease transmission should be less, thereby increasing the safety of allograft use. These newer techniques could potentially decrease the need for graft irradiation and other sterilization techniques that many affect allograft properties.

Surgeons can minimize complications associated with infected allograft tissue by only using tissue processed from a tissue bank accredited by the American Association of Tissue Banks (AATB). It is imperative that surgeons know the source of their allograft tissue, particularly if they rely on the hospital or a surgery center to obtain the allograft tissue for their patients.

http://www.aaos.org/news/bulletin/aug07/clinical1.asp

http://www.medscape.com/viewarticle/491618

http://books.google.ca/books?id=2qq56LYomagC&pg=PA397&lpg=PA397&dq=RISK+OF+TRANSMITTED+DISEASE+WITH+ALLOGRAFTS&source=bl&ots=cU9MnbRoBB&sig=KSY91n5fKiD2lVksKSU6A8vG204&hl=en&ei=iqHuTMmwAcnFnAf0u5jwCg&sa=X&oi=book_result&ct=result&resnum=10&ved=0CFIQ6AEwCTge#v=onepage&q=RISK%20OF%20TRANSMITTED%20DISEASE%20WITH%20ALLOGRAFTS&f=false